Protecting Competition in Eye Care

In the U.S. health care system, patients are often too far removed from the payment for specific services, which results in a lack of price transparency and consumer choice. However, there are pockets of health care that do allow patients to shop for the best prices. Eye care, specifically the buying of contact lenses, is one such area. It is important to protect this competition. 

Nearly 45 million Americans use contact lenses, which are considered “medical devices” that require a prescription to access. Patients can see the doctor of their choice, and after receiving a prescription for contact lenses, they are guaranteed the right to fulfill that prescription from their retailer of choice. They can buy from their doctor’s office, online retailers, or big box stores. This has not always been the case; in the early 2000s, Congress and the Federal Trade Commission (FTC) stepped in to protect patient choice and competition. 

The FTC’s contact lens rule (CLR) is designed to spur competition in access to contact lenses. In doing so, it guarantees patient choice and lowers prices. A simple mechanism in the CLR accomplishes this —requiring all prescribers to provide a patient with their prescription immediately after a contact lens fitting or renewal. To protect patient safety, the patient or prescriber must directly supply a retailer with the prescription. If this does not occur, the patient’s retailer of choice must verify the prescription directly with the prescriber via phone, fax, or email. The FTC requires retailers to gather and share specific information with the prescriber to ensure they provide the patient with the correct prescription.

Despite over two decades of success, including the FTC reviewing and updating the CLR,  Congress is now revisiting the process of how Americans get access to contact lenses. In July of 2025, Congress introduced HR 4282, the Contact Lens Prescription Verification Modernization Act. The bill, which has been championed by prescribers, would add more administrative burden to the process of accessing contact lenses. The additional burden would likely push patients back to buying from their prescriber, instead of shopping for the best prices from other retailers. 

If enacted, the bill would ban automated phone prescription verification. Verification by phone, email, or fax is merely a backstop for when prescribers fail to present patients with their prescription at the end of their fitting or renewal. The claim behind the bill is to make the verification process simpler, but the FTC has already addressed the effectiveness of using automated calls when updating the CLR in 2020. They found automated calls work in the majority of cases and were an efficient form of verification. This bill would create a bottleneck in the process by requiring retailers to use more expensive and less efficient methods to verify prescriptions, such as faxing or emailing. Instead, Congress and the FTC should address prescribers who are not complying with the CLR, consequently requiring verification. This does not serve patients by lowering prices, creating more efficient processes, or increasing access; all it does is complicate the process.

As inflation and the cost of health care continue to increase, patients are forced to make tough decisions between paying for health care services versus other living expenses. Congress should be focused on improving competition in health care, not complicating processes that have been working well for consumers for decades. 

The Contact Lens Prescription Verification Modernization Act does not meaningfully improve eye care for patients but will impact the market competition for contact lenses. With the health care market continuing to consolidate at an alarming rate, it is essential for Congress to prioritize bills that improve patients’ safety, access, and choice while not overburdening patients, providers, and retailers with administrative steps. Congress should move on from this bill.  

Another Month in RFK Jr.’s Vaccine Conspiracy Theories

This time last year, Secretary of Health and Human Services Robert F. Kennedy Jr. was signaling his plan to dismantle America’s mechanisms around vaccine safety and access. While there were still traces of hope that Congress would provide actual oversight over Kennedy, these efforts have so far turned out to be more performative than authoritative. Congress needs to step up and use its constitutional authority to provide adequate oversight before Trump and Kennedy push the U.S. further into a wholly preventable public health crisis. 

Luckily, the courts have paused the worst of Kennedy’s actions. The courts halted a revamped childhood vaccine schedule Kennedy pushed through in the shadows as well as his attempt to stack a crucial advisory panel with vaccine skeptics. Even as they are repeatedly told their actions are illegal, Kennedy and Trump continue to push forward their conspiracy theories and anti-vax agenda. 

Despite data showing a once unthinkable measles outbreak continues to expand, Trump, with Kennedy’s direct support, issued a new executive order (EO) earlier this month. The EO creates confusion for families, providers, and communities by changing how and for whom certain vaccines are recommended. More than anything, this new action shows how little the men leading public health in this country actually know about these topics. With this anti-science EO, Trump and Kennedy are causing more harm than good by providing parents with a message that diverges from what pediatricians are saying.

At the press conference announcing the new executive order, the president reiterated one of his favorite fabrications: the MMR (measles, mumps, and rubella) vaccine is safer when split into three separate shots. Here’s the thing, though — U.S. pharmaceutical companies don’t manufacture, and there is no FDA approval for three separate vaccines. It is functionally impossible to separate these vaccines right now. So why would the president throw this idea out? Besides ignorance, it is a tactic to create confusion for parents and complicate adherence to the vaccine schedule. By unnecessarily separating these vaccines, people will be less likely to complete all the steps. 

One rationale for the new executive order was that they “only” moved some of the vaccines to the shared clinical decision-making designation, not removing vaccine recommendations completely. The president and secretary justify this by claiming this allows providers and parents to have a conversation about the vaccines, not to deter them. This shows, again, a lack of understanding of these systems. 

The vaccine schedule does not demand — or even recommend — a child be given a vaccine without a discussion with the parents. Shared clinical decision-making is intended for care decisions where the medical evidence is not clear, and there are multiple treatment options. Vaccines, especially Kennedy’s claim that they are tied to autism, have decades of research and evidence. Autonomy in health care is necessary, and the recommended vaccine schedule had provided autonomy well before Kennedy started changing it. 

These misinformed decisions are not just symbolic; they are already changing individual vaccination decisions throughout the U.S. Data for the 2025-2026 school year shows a new record high of vaccine exemptions for school-aged children. The majority of counties in the US do not achieve herd immunity in kindergarten classrooms. Meaning the community level of immunity to minimize the spread of an infectious disease has not been reached, leaving those who are unable to be vaccinated for a variety of reasons unprotected. Trump and Kennedy’s anti-vax agenda creates nothing but confusion and is tied to this dangerous collapse in vaccination rates. 

Kennedy and Trump’s policies are being evaluated currently by the committee that monitors the US’s measles eradication status by reviewing the CDC’s annual report on measles. Although a decision will not be made until November, the US is in the midst of the worst outbreak of measles in decades and is unlikely to retain the status of measles elimination. The loss of this status may sound like an administrative designation, but it indicates a larger problem of potential societal and economic harms. For example, one case could have a societal cost (e.g., loss of productivity, cost of care) of $47,000, not to mention the potential confusion for places such as childcare centers when an outbreak occurs. We have solutions to prevent these harms, but Kennedy is choosing not to use them.

To end last week, Kennedy published a Request for Information (RFI) to gather feedback about the categories used on the childhood vaccine schedule. This move appears to exclude the Advisory Committee on Immunization Practices (ACIP) and the scientific experts of the CDC by accepting the changes from the executive order as finalized. In addition, by using an RFI, as opposed to a proposed rule, HHS is not required to respond to individual responses or concerns submitted. So this is merely a mirage of gathering public feedback.    

The biggest fault of vaccines is that they are a victim of their own success. Many people do not fear polio, measles, or other vaccine-eradicated diseases because they have not seen the harm firsthand. Most people do not know someone who spent their life in an iron lung after contracting polio, the long-term brain damage caused by measles, or a child with advanced liver damage due to hepatitis B. 

However, using herd immunity to protect the community against infectious disease is a long-held American idea that dates back to George Washington’s command of the Continental Army. Giving up on it now is not only deeply un-American, but it is also an abdication of duty by the president and HHS secretary to promote the general welfare of this country. Congress needs to be a check on the executive branch by holding oversight hearings to better understand how these vaccine decisions are being made and pass the Family Vaccine Protection Act. Americans deserve to be provided with sound, evidence-based health recommendations from their government.

Guenther and Ware for Real Clear Science: The Trump Administration’s Most Dangerous Attack on Science Yet

Donald Trump’s assault on the American scientific enterprise has been death by a thousand cuts. But the latest push from the Office of Management and Budget (OMB) may just be the kill shot. 

OMB proposed a rule to “improve government-wide policies and requirements related to the management of grants, cooperative agreements, and other forms of assistance.” This rule will impact funding to over 40 different federal agencies, ranging from NASA and HHS to the National Foundation on the Arts and the Humanities to the Peace Corps by – among other things – giving political appointees veto power over grant funding applications both when they are initially considered and once the grant period has commenced. The final rule is expected to be published any day now to tee it up to go into effect on October 1.

The rule’s stated goals are to enhance accountability, transparency, and oversight of federally funded scientific research, which sound innocuous. In reality, it does the opposite by pushing the grantmaking process behind closed doors and politicizing practically every element of American research — not to mention implementing requirements that go against the law in a host of different ways. Just to provide one example, as the American Association of Universities put it, “Congress has repeatedly directed federal agencies to fund university research in ways that explicitly require the kind of demographic-conscious program design the proposed rule would prohibit.”

To put the importance of the scientific enterprise in context, according to economists at the Federal Reserve Bank of Dallas, “government-funded [research and development] (R&D) accounts for roughly one quarter of all business sector productivity growth since World War II.” Concerns about this rule aren’t centered on protecting the Ivory Tower — they’re about the economy, competitiveness with China, and, as the Democratic leaders of the House Energy and Commerce Committee highlighted, Americans having access to groundbreaking medical treatments first.

Read more in Real Clear Science

Who is Hiring Medicaid Recipients?

Being poor in America is hard. Temporary Assistance for Needy Families (TANF) has virtually disappeared in many states. Safety net programs such as Medicaid and SNAP have strict income limits, with participants coming under increased pressure to work. Indeed, a KFF study found that as of 2023, roughly two-thirds of nondisabled non-elderly (NDNE) Medicaid recipients had paid employment.  

That puts many low-income people in the tricky position of threading a very thin needle. A single mother, for example, may be trying to balance time spent attending community college and raising kids, while working just enough hours to earn some money without violating the Medicaid income limits. A full-time job which provides health care coverage would be best, of course — but finding one that pays enough to cover childcare may not be possible without more schooling. 

In this context, the most attractive employers for Medicaid recipients may be those which offer a lot of flexibility in working hours to help stay under the income limits,  with the possibility of jumping to full time work when appropriate. A new study from the GAO analyzed data from a small number of selected states and identified the top employers of NDNE Medicaid and SNAP recipients in those states. These included large private employers such as Walmart, Amazon, and Fedex; universities and healthcare systems such as Indiana University, Brown University, Mass General Brigham, MaineHealth, and Emory Healthcare; and public entities such as the Commonwealth of Massachusetts,  the U.S. Post Service, and the Georgia Department of Human Resources. 

In many ways, being named on the GAO’s list of top employers who hire Medicaid recipients is a badge of honor. Especially with work requirements tightening up in 2027, we need to encourage more employers to hire Medicaid recipients, not discourage them.   

It’s not unreasonable to expect that large employers should offer full-time employees access to healthcare. But note that the GAO’s employer analysis contains absolutely no direct information about whether the Medicaid recipients at  these large organizations were in full-time jobs. As part of the same paper, the GAO did a separate statistical analysis of the national workforce which suggests that most wage-earning nonelderly Medicaid recipients work for smaller companies, and less than half work full-time, full-year jobs. 

Indeed, people — Medicaid recipients or not — often seek out flexible work because they are caregivers, military spouses, students, retirees supplementing Social Security, parents of school-age kids, or have some other life circumstances which require that flexibility. These types of opportunities allow people to be productively employed when they might otherwise be excluded from work altogether. 

New PPI Report Details RFK Jr.’s Record of Breaking Health Promises

WASHINGTON (May 28, 2026) — The Progressive Policy Institute (PPI) released a new report today documenting how Health and Human Services Secretary Robert F. Kennedy Jr. has dismantled scientific safeguards and broken commitments to Congress, undermining legitimate efforts to improve America’s public health.

“Curing MAHA: How to Protect Public Health After Kennedy,” authored by PPI’s Director of Health Care Policy Alix Ware, reveals how, instead of creating a credible public health initiative, Kennedy has exploited the fears of Make America Healthy Again supporters to advance discredited medical theories and consolidate power without oversight.

Kennedy promised Republican senators during his confirmation hearing that he would respect the government’s existing vaccine safety system and follow accepted science. Instead, the report documents how he has systematically removed scientific experts from key agencies, defunded critical medical research, and altered health guidance based on unfounded claims about autism, all while cutting nearly a quarter of the HHS workforce.

The damage extends across three critical areas:

  • Kennedy endorsed the reckless decimation of federal health agencies, eliminating staff who collect and analyze national health data and ethics professionals.
  • Kennedy has divorced health guidance from science, peddling long-debunked theories about vaccines and autism that have already influenced medication use among pregnant women.
  • Kennedy has removed oversight mechanisms designed to ensure agency decisions rest on evidence rather than ideology, firing the CDC director who resisted his demands and stacking federal advisory committees with vaccine skeptics.

“Many Americans have legitimate concerns about our health system that deserve serious attention,” said Ware. “But Kennedy’s approach has squandered an opportunity to address them. He promised to follow gold standard science and instead has weaponized federal health agencies to serve his personal beliefs.”

Even supporters of MAHA’s original goals are disappointed. Polling shows 47% of voters who backed the movement say the administration has not done enough to make America healthy again. Kennedy’s actions have eroded public trust in federal health guidance: confidence in the CDC’s vaccine schedule has fallen from 71% to 61% in under a year.

The report recommends that Congress take four steps to repair the damage and prevent similar abuses in the future:

  1. Increase transparency and accountability of federal advisory committees to ensure decisions are based on scientific evidence.
  2. Modernize the federal workforce while rebuilding trust with career employees so that skilled scientists and health professionals are not afraid to work in government.
  3. Limit the use of acting officials to prevent political appointees from bypassing Senate confirmation and accountability.
  4. Develop a long-term, non-partisan plan to address chronic disease grounded in evidence and expertise rather than shifting with each administration.

Read and download the report here.

Founded in 1989, PPI is a catalyst for policy innovation and political reform based in Washington, D.C. Its mission is to create radically pragmatic ideas for moving America beyond ideological and partisan deadlock. Find an expert and learn more about PPI by visiting progressivepolicy.org. Follow us at @ppi.

###

Media Contact: Ian O’Keefe – iokeefe@ppionline.org


Curing MAHA: How to Protect Public Health After Kennedy

INTRODUCTION

When President Trump nominated Robert F. Kennedy Jr. to become his secretary of health and human services, it was possible to conjure a few faint reasons for optimism. Yes, his well-known rejection of mainstream vaccine science and general penchant for medical quackery were frightening. But Kennedy also offered one fundamentally correct critique of America’s health approach: For years, we have done far too little to combat our country’s epidemic of chronic disease through prevention, instead relying on expensive treatments once people become sick.

To win confirmation, Kennedy gave some ground to his skeptics, promising Republican senators he would respect the government’s existing vaccine recommendation system and follow accepted science. Once in the cabinet, Kennedy’s Make America Healthy Again (MAHA) agenda was kicked off with the president signing an executive order vowing to tackle chronic illness through “fresh thinking on nutrition, physical activity, healthy lifestyles, over-reliance on medication and treatments, the effects of new technological habits, environmental impacts, and food and drug quality and safety.” On paper, all of these were worthy goals. If Kennedy had stuck to them in a remotely reasonable way, it was conceivable he might even have found bipartisan buy-in for parts of his MAHA agenda.

Unfortunately, Kennedy’s tenure at HHS has confirmed the worst concerns of his critics, and then some. He has thrown America’s major health agencies into turmoil by firing highly experienced scientists and health professionals, defunding vital medical research, and making unfounded claims about autism, all while emulating President Trump by ignoring checks and balances on his authority. His fixation on voodoo science and conspiracy theories is wasting the opportunity he had to make progress on a MAHA agenda that the country could overwhelmingly support.

In recent months, the Trump administration has made moves seemingly aimed at reining Kennedy in, due to the sheer unpopularity of his stances on issues like vaccines. Some Republican members of Congress have also started to push back against the secretary. But a new Congress will bring additional opportunities to hold him accountable for his record of broken promises. In this paper, we will review the most damaging aspects of the secretary’s record in depth, while outlining steps lawmakers should take to curb his abuses and prevent similar ones in the future. Those include:

  • Increasing the transparency and accountability of federal advisory committees
  • Modernizing the federal workforce while rebuilding trust with potential career employees
  • Limiting the use of acting officials for Senate-confirmed roles
  • Creating a long-term non-partisan plan to make America healthy

While curtailing the secretary’s destructive overreach is essential, it would be a mistake to ignore the genuine grassroots political energy the MAHA movement has harnessed. Many of its goals command overwhelming support among voters, at least when framed in general terms. Rather than attempt to return to the old status quo of health, critics would be wise to divorce Kennedy from the concerns of MAHA champions and point out how Kennedy’s own management of HHS is foiling the ambitions he vowed to pursue. America’s legions of MAHA supporters have some valid concerns about our health system. But they need a different sort of champion.

Read the full report.


A Smarter Path Forward on Premium Tax Credits

Two weeks ago, Congress let another deadline pass by, failing to act on the year-end expiration of tax subsidies that help millions of Americans afford health insurance. This legislative failure has already begun to hurt Americans, with 1.4 million fewer people enrolling in health insurance plans on the federal marketplace. And despite months of legislative attention, Congress is no closer to a real solution to reduce health care costs for the American people.

Most Democrats are still demanding a three-year extension of the pandemic-era subsidies, with no way to pay for it. But while their plan did advance in the House, it stands no chance in the Senate. Meanwhile, most Republicans are still clueless on health care, unable to offer any real solutions to reduce costs. Even the Senate’s “pragmatic dealmakers” have failed to make progress, with deliberations stuck in the mud. 

It’s time for a compromise like the one that PPI proposed in September. Our plan would strike a sensible middle ground, preserving many benefits for low-income Americans but saving money by targeting subsidies to those who need them most. The subsidies would also be permanent, paid for by cracking down on unfair practices that insurance companies and large hospitals use to overcharge the federal government.

Congress Shouldn’t Repeat the Mistakes that Got Us Here

To understand why a compromise is needed, it’s worth recalling how these enhanced subsidies came to be. In 2021, Democrats temporarily expanded the Affordable Care Act’s (ACA) health insurance subsidies as part of their pandemic relief bill. The enhanced tax credits were designed for a health emergency, and were therefore unusually generous. But once the pandemic had subsided and the tax credits were set to expire in 2022, many Democrats argued that they should be made permanent.

To some extent, these Democrats had a point — the enhanced subsidies provided real financial relief and helped push America’s uninsured rate to a record low. They also eliminated the ACA’s “benefit cliff,” which caused enrollees to lose all of their benefits if their income rose above an arbitrary threshold. But moderate Democrats realized that the pandemic-era subsidies were deeply flawed. The benefit formula was skewed toward higher-income enrollees, with some families making over $300,000 per year being eligible for taxpayer support. And a permanent extension would have cost roughly $300 billion over ten years, adding fuel to our ballooning national debt.

At the time, my colleagues at the Progressive Policy Institute called for a permanent compromise. But instead, Congress chose the worst possible approach, extending the full pandemic-era subsidies for three years. Rather than solving the problem, lawmakers guaranteed that it would return in 2025.

A Better Way Forward

While Congress failed to meet its 2025 deadline for action, a bipartisan group of Senators is still hoping to find a solution (and make it retroactive). The details of this plan are still unfinished, but negotiators will surely be tempted to propose a temporary, deficit-financed version of the subsidies — nothing more than a repacked version of the ideas that have failed to gain traction for months. Instead of rehashing failed ideas, negotiators should get behind a sustainable and permanent solution to make health care more affordable.

If Senators are willing to take the second approach, they should turn to PPI’s proposal, which would enact a more affordable version of the subsidies and pay to make them permanent. Our plan would preserve free health insurance for Americans in poverty and would provide more generous support than the original ACA for people earning up to 350% of the federal poverty level. It would also eliminate the ACA’s benefit cliff, meaning middle-income Americans wouldn’t immediately lose all of their tax credits if they receive a modest raise. Crucially, the plan would cost just half as much as the pandemic-era subsidies, generating the greatest savings by scaling back subsidies for upper-income enrollees that don’t need them.

This proposal would be fully paid for through savings in the health-care system. It cuts costs by adopting site-neutral payments in Medicare, ensuring that the program pays the same rate for a procedure regardless of whether it is performed in a doctor’s office or a hospital. It would also crack down on upcoding in Medicare Advantage, the practice in which private insurers make their patients appear sicker than they really are in order to secure higher government reimbursements.

Not only are these proposals smart policy, but they would also undercut the strongest argument against the subsidies — that subsidies, on their own, do not drive down the underlying costs of health care. By cracking down on large hospital systems and insurance companies that siphon money from our medical system, these reforms could do more to reduce costs than any law since the Affordable Care Act.

The stakes are too high for politicians to waste time on unrealistic proposals or temporary fixes. It’s time for Congress to get behind a credible solution to reduce health-care costs and provide long-term security for the millions of Americans who purchase health insurance through the ACA’s marketplace.

PPI Warns That Hospital Takeovers of Physician Practices Are Driving Up Costs and Reducing Patient Access

WASHINGTON — The Progressive Policy Institute (PPI) today released a landmark report detailing how a wave of hospital acquisitions of independent physician practices is restricting consumer access to health care, driving up prices and costs, and accelerating the erosion of physician autonomy. The study, “Fixing a Broken System: Policy Responses to Hospital Acquisitions of Physician Practices That Limit Health Care Access for U.S. Consumers,” analyzes national data from 2017 to 2024 and reviews more than 70 economic studies to unveil the mounting consequences of unchecked vertical consolidation.

Led by Diana Moss, Vice President and Director of Competition Policy, with coauthors Alix Ware, Director of Health Care Policy, and Lief Lin, Policy Research Fellow, the report shows that the share of independent physician practices has fallen sharply across the country as hospitals and large health systems absorb local providers. In many specialties, independent practices declined by up to 40%, with the steepest losses occurring in general surgery, oncology, and cardiology. Rural communities were hit hardest, experiencing a 34% decline in independent practices, compared to 22% in urban areas.

“The collapse of independent physician practices is not an isolated trend. It is a major structural shift that threatens affordability, choice, and the long-term resilience of our health care system,” said lead author Diana Moss. “Hospitals are acquiring local practices at a lightning pace, and consumers are paying the price through higher bills and fewer options.”

Key findings from the report include:

  • Most economic studies show hospital acquisitions of physician practices lead to higher prices and increased spending, with average price hikes of 14% and some exceeding 30%.
  • Nearly half of post-acquisition price increases stem from hospitals exploiting Medicare’s site-of-service payment differentials.
  • Large health systems are driving consolidation, with some expanding their ownership of  physician practices by several hundred percent between 2017 and 2024.
  • Current antitrust enforcement is far below average for the hospital and ambulatory health services sectors, despite mounting evidence of harm.

PPI’s analysis also underscores how state-level policies such as certificate of need (CON) laws and certificate of public advantage (COPA) agreements often exacerbate consolidation by raising barriers to entry and shielding hospital mergers from antitrust scrutiny. States without CON laws show significantly higher survival rates for independent physician practices and more new entry.

To address the crisis, PPI calls for a five-part federal and state policy strategy:

  1. Enact site-neutral Medicare payment reform to eliminate the financial incentives driving hospital purchases of physician practices.
  2. Strengthen antitrust enforcement to scrutinize hospital acquisitions of physician practices and challenge harmful transactions.
  3. Consider reforms to state CON and COPA laws that restrict competition and reinforce hospital market power.
  4. Protect physician autonomy by modernizing governance, compensation rules, and related federal policies that limit physician-led models.
  5. Strengthen rural health care access through targeted reinvestment, value-based care, and innovative delivery models.

“This is a moment for urgent, bipartisan action,” said co-author Alix Ware. “If policymakers fail to reform the incentives that fuel consolidation, patients will face even higher costs and fewer choices. The time to intervene is now.”

Read and download the report here.

Founded in 1989, PPI is a catalyst for policy innovation and political reform based in Washington, D.C. Its mission is to create radically pragmatic ideas for moving America beyond ideological and partisan deadlock. Find an expert and learn more about PPI by visiting progressivepolicy.org. Follow us @PPI. 

###

Media Contact: Ian O’Keefe – iokeefe@ppionline.org

Fixing a Broken System: Policy Responses to Hospital Acquisitions of Physician Practices That Limit Health Care Access for U.S. Consumers

The Progressive Policy Institute’s new study unpacks ongoing hospital acquisitions of independent physician practices in the U.S. This vertical integration reduces vital competition in critical health care markets. The result is reduced access to health care for Americans, through higher prices and spending, less choice in health care delivery models, and the erosion of physician decision-making autonomy in patient care.

The loss of independent physician practices (IPPs) from hospital and health system acquisitions is a major component of the broader absorption of physician practices into corporate owners such as commercial health insurers, private equity firms, and retail conglomerates such as pharmacy chains. Between 2019 and 2023, the percentage of IPPs owned by hospitals/ health systems and other corporate entities increased from 39% to 59%, while the percentage of physicians employed by these same entities increased from 62% to 78%.

American consumers are already struggling with less access to health care, including what they pay, how easily they can obtain health care services, whether they have choice in facilities and providers, and the overall stability and resiliency of the health care system. The looming disappearance of the IPP compounds this formidable problem.

A review of 70 economic studies shows that hospital acquisitions of IPPs have myriad adverse effects. This includes higher prices and health care spending and the loss of decision-making autonomy for physicians because of changed corporate financial objectives. The elimination of the IPP as a vital health care delivery model has also reduced access to health care by eliminating an important source of choice for consumers.

PPI’s study advances the state of policy analysis regarding the impact of consolidation by tracking the recent decline in IPPs in the U.S., against the backdrop of economic evidence that acquisitions by hospitals harms consumers. PPI looked at the decline in IPPs across nine major medical specialties at the national, state, regional, and rural vs. urban levels in 2017 and 2024. The results of PPI’s study highlight several major takeaways:

  • There is mounting economic evidence that vertical integration of hospitals and IPPs increases prices and spending.
  • The U.S. health care system has sustained a significant decline in IPPs as a result of being acquired by hospitals. These decreases range from 4% to 42% across nine medical specialties.
  • Hospital acquisitions of physician practices have an outsized impact on rural areas of the U.S. IPPs in rural areas declined by 34%, versus only 22% in urban areas and were the highest in the western Midwest and New England.
  • Hospitals focus on acquisitions of larger physician practices in establishing or scaling up their market position in a medical specialty area. Large IPPs decreased by 45% and medium size IPPs declined by 36%.
  • Some of the largest health systems in the U.S. are the most active acquirers of physician practices, exacerbating already high levels of concentration in hospital and medical specialty markets.

When considered in light of evidence from existing economic studies showing that hospital acquisitions of IPPs increase prices and spending, policy approaches to addressing the precipitous decline in IPPs in the U.S. take on new urgency. For example, studies show average price increases of about 14%, with some increases as high as 33%, and higher increases in markets where a hospital has a dominant position. Evidence also shows that approximately 45% of price increases are due to exploitation of Medicare site-of-service reimbursement rules. The majority of studies also show that hospital acquisitions of IPPs result in increased spending.

PPI’s study concludes that better policies, achieved through comprehensive policy reform, are needed to address the loss of IPPs in the U.S. In framing this approach, PPI unpacks the multiple, flawed policies that bear directly on the anticompetitive effects of hospital acquisitions of physician practices. These policies have collectively failed to rein in consolidation and, in some cases, even incentivize it.

Major policy areas that bear directly on hospital acquisitions of IPPs and their outcomes include: (1) Medicare reimbursement rules that incentivize vertical integration, (2) below average merger enforcement, (3) state regulations that limit market entry, immunize hospitals from antitrust liability, and encourage gaming of the rules and exceptions to facilitate consolidation; (4) the absence of coherent policy to address a loss of physician autonomy that results from selling an IPP to a hospital; and (5) the need for a policy on health care access for rural areas.

Because of the lightning speed at which hospitals have acquired IPPs over the last two decades — and especially in the last eight years covered by PPI’s study — policymakers are now working against the clock. PPI’s “call to action” is for policy reform to protect American consumers and physicians, and improve access to the health care system. This effort should garner broad, bipartisan support from Congressional sponsors of site-neutral payment reform, state lawmakers, and federal and state antitrust enforcers. PPI recommends a five-part plan to address rampant hospital acquisitions of IPPs.

  • Pass federal legislation for site-neutral payment reform to remove the major incentive that drives hospital acquisitions of IPPs.
  • Strengthen federal and state antitrust enforcement to ensure that anticompetitive hospital acquisitions of IPPs are blocked or adequately remedied.
  • Consider reforming or revisiting state laws that govern hospital entry and shield powerful companies from antitrust scrutiny.
  • Protect physician autonomy by advancing policies that focus on quality of care, physician leadership in governance in hospital settings, physician-led initiatives, and telemedicine.
  • Develop policies to ensure access to health care in rural areas by reinvesting in rural hospitals, moving to value-based care, and supporting innovative business models and technology use.

Read the full report.

A Better Way to Fix the Pandemic Premium Tax Credit Than Income Caps

One of the biggest obstacles to ending the government shutdown is partisan disagreement about how to address the looming expiration of a pandemic-era expansion of the Affordable Care Act’s (ACA) premium tax credit (PTC). Established in 2014, the PTC gave subsidized health insurance to Americans who didn’t receive it through their employer or the government. The American Rescue Plan (ARP) made this program substantially more generous, including to higher-income households that were never supposed to receive assistance under the original ACA. Democrats want to continue the pandemic PTC expansion in its entirety, while most Republicans want it to expire.

A bipartisan consensus appears to be emerging that the way to better target assistance moving forward and end the shutdown is to impose an income cap on eligibility for the PTC. Unfortunately, this compromise would restore the biggest flaw in the original ACA design that ARP solved: the benefit cliff. Before ARP expanded the PTC, households with income greater than 400% of FPL were not eligible for the ACA subsidy. That meant a single extra dollar of income could trigger thousands of dollars in higher premiums — an abrupt cutoff that discouraged work. Bringing back an income cap today would leave households vulnerable to sudden increases in health-care costs as a penalty for working. 

Instead of repeating past mistakes, a better approach would be to establish a gradual phase-out of benefits for households as their income increases. This would smooth out the benefit cliff established under the ACA and avoid giving windfalls to high-income households.

Under PPI’s preferred approach, households with incomes under 300% of FPL would be eligible for the same expanded subsidies next year that they are today. But rather than capping health-care premiums at a certain percentage of recipients’ income, premiums would steadily increase as household income increases. As a result, high-income households’ subsidies would taper off as their earnings increase, thus reducing unnecessary benefits for high earners without recreating the benefit cliff. Subsidies would also fully phase out at lower income levels than they do today.

If lawmakers are concerned about high-income households still qualifying for subsidized health insurance, the best solution is to adjust the phase-out such that a household’s premiums are set to increase starting at a lower level of income. Accordingly, PPI proposes that the phase-in threshold gradually decreases for each of the next two years — similar in concept to a recent proposal from Sen. Mike Rounds (R-S.D.) to gradually phase down the credits back to pre-pandemic levels. But PPI’s proposal preserves free health insurance for families in poverty while still requiring reasonable contributions from middle-income households that can afford it, and lowering benefits for high-income households that don’t need the support.

Along with providing generous support to those who don’t need it, the other problem with simply extending the pandemic PTC expansion is that it is expensive, costing at least $23 billion per year. Rather than cutting health-care costs, it merely shifted the burden onto taxpayers. Fortunately, there are solutions that will both pay for the proposed expansion — letting taxpayers off the hook — and cut health-care costs in the long run. 

Medicare Advantage, which allows seniors to receive their Medicare benefits from private insurers, costs taxpayers tens of billions of dollars per year because certain loopholes allow insurance companies to make patients appear sicker than they actually are, which artificially increases their government reimbursements. The No UPCODE ACT would end this practice and save at least $125 billion over 10 years, according to the Committee for a Responsible Federal Budget. Medicare also currently pays far more for services provided in hospital outpatient departments than in independent physician offices, a disparity that encourages hospitals to buy up clinics and drive consolidation — raising costs for patients and taxpayers alike. Adopting site-neutral payments could save $175 billion over the next decade.

Together, these two reforms would fully offset the cost of PPI’s proposed PTC expansion extension on a permanent basis. By eliminating the benefit cliff under the original ACA and establishing gradual phase-outs, PPI’s plan would prevent middle-class families from experiencing a sudden loss in benefits, ensure the poorest families remain protected, and avoid unnecessary tax subsidies for high-income households. These values reflect the goals of the ACA: affordable coverage and strong work incentives. Now is an opportunity for Democrats to push Republicans to adopt thoughtful reforms to the PTC. Millions of Americans are depending on them to get it right.

PPI Proposes Pragmatic Plan to Reform ACA Premium Tax Credits and Curb Skyrocketing Health-Care Costs

WASHINGTON — As partisan disagreements over extending pandemic-era premium tax credits (PTC) threaten a government shutdown next week, the Progressive Policy Institute (PPI) today released a pragmatic plan to protect families from steep premium hikes while reining in unsustainable federal spending on health care.

“A Pragmatic Path Forward on Premium Tax Credits,” authored by Tim Sprunt, Policy Analyst at PPI’s Center for Funding America’s Future, and Ben Ritz, PPI’s Vice President of Policy Development and Director of the Center for Funding America’s Future, charts a fiscally responsible middle path between Democrats who want to make pandemic-era subsidy expansions permanent and Republicans who want to let them expire abruptly.

PPI’s analysis finds the 2021 expansion of the Affordable Care Act (ACA) premium tax credits provided critical benefits during the COVID-19 pandemic and corrected structural problems with the original design, such as a “benefit cliff” that discouraged work among upper-middle-income households. However, the expansion also made the ACA significantly more regressive and would cost $380 billion if continued for the next decade, showering unnecessary benefits to high-income households while doing nothing to address the underlying drivers of rising health-care costs. 

“Democrats must stop reflexively seeking to extend every Biden-era fiscal policy, no matter how poorly designed, and Republicans must stop seeking to cut support for American health care at every available opportunity,” said Sprunt. “PPI’s proposal offers a pragmatic path between the two extremes.” 

Specifically, PPI proposes to gradually move from the pandemic PTC structure to one that splits the difference between it and the structure originally established by the ACA. Free coverage would be permanently preserved for families at or below 100% of the federal poverty level, while higher-income households would eventually be required to pay premiums roughly halfway between the pandemic-era expansion and the original ACA. This structure would also permanently smooth the benefit cliff that significantly increased premiums for anyone just outside the original PTC’s eligibility range. 

PPI’s proposed PTC would cost roughly half as much as a permanent expansion of the pandemic PTC. But crucially, PPI’s proposal would fully pay for these targeted subsidies by pairing them with real reforms to attack the drivers of rising health-care prices. These reforms include:

  • Cracking down on Medicare Advantage upcoding: Adopting key provisions of the bipartisan No UPCODE Act would save at least $125 billion over 10 years by preventing insurers from inflating risk-adjustment payments.
  • Expanding site-neutral payments: Curtailing the practice of paying hospitals more than independent clinics for identical services could save Medicare $175 billion over the next decade and discourage the consolidation of providers that leaves all Americans with fewer health-care choices.

“PPI’s proposal shows pragmatic Democrats are serious about cutting medical costs rather than simply increasing government spending,” said Ritz.

Read and download the new proposal here.

Launched in 2018, the Progressive Policy Institute’s Center for Funding America’s Future works to promote a fiscally responsible public investment agenda that fosters robust and inclusive economic growth. To that end, the Center develops fiscally responsible policy proposals to strengthen public investments in the foundation of our economy, modernize health and retirement programs to reflect an aging society, transform our tax code to reward work over wealth, and put the national debt on a downward trajectory.

The Progressive Policy Institute (PPI) is a catalyst for policy innovation and political reform based in Washington, D.C. Its mission is to create radically pragmatic ideas for moving America beyond ideological and partisan deadlock. Learn more about PPI by visiting progressivepolicy.org.

Follow the Progressive Policy Institute.

###

Media Contact: Ian O’Keefe – iokeefe@ppionline.org

A Pragmatic Path Forward on Premium Tax Credits

INTRODUCTION

Democrats have made extending a pandemic-era expansion of the Affordable Care Act’s (ACA) premium tax credit (PTC) their central demand in this year’s government funding negotiations, going so far as to threaten a government shutdown next week if Republicans do not attach it to a short-term funding bill. The pandemic PTC served an important purpose in the midst of the COVID-19 pandemic, helping reduce the cost of health insurance for households that did not have coverage through their employer or another government program at a time when workers were at heightened risk of losing their jobs or experiencing a medical emergency. It also corrected some long-standing problems with the PTC’s original structure, such as a “benefit cliff” that discouraged earnings by cutting benefits off altogether for households that made even one dollar more than the income eligibility limit.

Allowing the expansion to expire immediately in its entirety, as most Republicans propose to do, would be deeply damaging: the Congressional Budget Office (CBO) estimates that more than 4 million Americans could lose their health insurance when the pandemic PTC expires, while the Kaiser Family Foundation (KFF) estimates that out-of-pocket premium payments for enrollees on the individual insurance exchange marketplaces would rise by more than 75%.

But reflexively continuing the policy in its current form, whether through repeated temporary extensions or outright making it permanent, would also be unwise. The pandemic PTC provides substantial subsidies for households higher up the income ladder that go far beyond the program’s original intent. The extension is expensive, costing more than $20 billion per year — a cost Democrats never proposed to sustainably pay for, despite the national debt already being at historic heights. The tax subsidies it provides for a small slice of the population are significantly more costly than the tax subsidies from which most Americans benefit through employer-sponsored insurance. And perhaps worst of all, the pandemic PTC pumps more money into a broken and costly health-care system while doing nothing to tackle the true drivers of high prices.

PPI proposes a pragmatic path forward between these two extreme positions. Our proposed framework would gradually transition into a new PTC structure somewhere between the original PTC and the pandemic PTC — one that eliminates the benefit cliff without showering unnecessary tax subsidies on high-income households. Moreover, we propose to pair this policy with other changes that more than offset its cost to the federal budget while reducing the price of health care for taxpayers and patients alike.

THE PANDEMIC PTC MAKES THE ACA MORE REGRESSIVE AND EXPENSIVE 

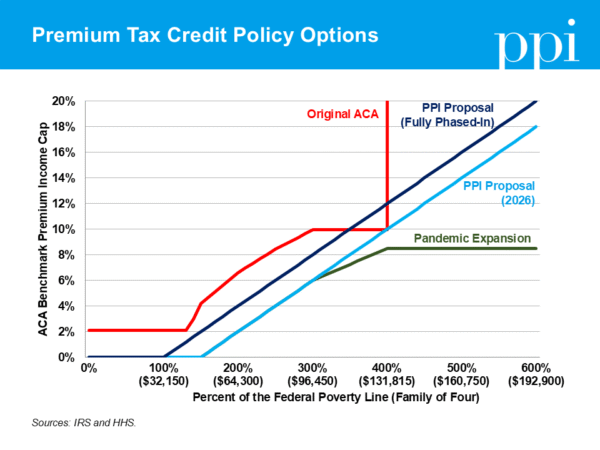
The original PTC was created by the ACA in 2014 to ensure that Americans who did not receive health insurance from the government or their employer could still afford quality health insurance. The ACA established thresholds for affordable health insurance based on income: for an American at the Federal Poverty Level (FPL), that affordability threshold could be just 2% of their income, while a middle-income American could be asked to pay up to 10%. If the cost of a benchmark plan exceeded this affordability threshold, enrollees with household incomes below 400% of FPL would receive a premium tax credit to make up the difference, which they could use to purchase any insurance plan on the ACA’s individual marketplace exchanges.

Even before the pandemic, the PTC had been unintentionally expanded through the practice of “silver-loading.” Insurers raised the cost of their middle-tier “silver” plans, which serve as the benchmark plans for PTC calculations, even though costs for both cheaper “bronze” and premium-tier “gold” plans on the exchanges remained unchanged. This practice increased PTC payments across the board, meaning households shopping on the exchanges could purchase a higher-quality plan using a smaller share of their income than the affordability threshold dictated.

The American Rescue Plan Act (ARP) passed during the COVID-19 pandemic then made the PTC significantly more costly — and less progressive — by lowering the affordability threshold across the board and making all households eligible for the PTC regardless of income for 2021 and 2022. The Inflation Reduction Act (IRA) extended this pandemic PTC expansion for an additional three years, but the policy is set to expire at the end of this year.

On the positive side, the pandemic PTC expansion fixed one of the greatest problems with the original PTC, whereby recipients could lose several hundred dollars of tax credits if they earned just one dollar over the 400% of FPL eligibility limit. It also made health insurance significantly more affordable during a once-in-a-century pandemic in which many people faced the sudden loss of income and insurance, along with higher medical risk.

But the pandemic PTC was never designed as a thoughtful long-term policy. Median-earning households are now expected to pay only two-thirds what the original ACA intended them to pay for a benchmark plan, and households with income below 150% of FPL are expected to pay no premium whatsoever. Even worse, the combination of a low benchmark premium cap with no eligibility limitation results in very high-income households receiving subsidies that were never intended for them when the ACA became law. In New York City, for example, couples with no children earning 1,000% of FPL — more than double the original PTC’s eligibility limit — are currently eligible for a PTC of more than $3,000 per year.

Those costs all add up: today, the average annual subsidy for the 7% of Americans who are covered by ACA exchange plans is $6,600 per person. That’s more than three times the tax subsidy that benefits people with employer-sponsored insurance, who make up more than half the population. These costs were worth the benefits during a global public health emergency, but they make little sense to continue as permanent policy — especially since supporters never determined a way to pay for them at a time when the government is running $2 trillion annual budget deficits.

Yet Democrats have rallied around legislation to extend the pandemic PTC permanently, which would cost approximately $380 billion over the next 10 years. At a minimum, they — and even a few Republicans — have argued in favor of extending the expiring subsidies for one year at a cost of $23 billion. But nobody has offered a coherent rationale for why it would make more sense to phase down subsidies next year than this year, especially considering that it is a midterm election year. A one-year extension with no adjustments or strings attached now simply sets the stage for more extensions in the future as a backdoor attempt to make the policy permanent.

Democrats must move beyond the desire they’ve shown in recent years to reflexively extend expiring pandemic-era policies that were never designed as long-term solutions. There is a better approach that prevents sharp premium hikes for families and eases into a more sustainable long-term policy while permanently fixing the benefit cliff and leaving health care more affordable for families than it was before the ARP.

PPI proposes to gradually move towards a reworked PTC structure that is more progressive and fiscally sustainable than the pandemic PTC, yet more fair than the original ACA. In 2026, households with incomes under 300% of FPL should be eligible for the same enhanced subsidies created by ARP. But the affordability threshold should continue to rise for higher earners rather than being capped at 8.5%. This will result in higher-income households gradually receiving lower subsidies as their income rises, and will fully phase out subsidies at lower income levels than they do today.

Then, over the next two years, the beginning of the phase-in for higher affordability thresholds would gradually move from 150% of FPL in 2026 to 100% of FPL in 2028. This compromise offers free health insurance for families in poverty while requiring modest contributions from middle-income households that can afford it and tapers off support for high-income households that don’t need it. Policymakers can choose at this point whether they would make the new subsidy structure permanent or let voters decide its future in the 2028 elections. Based on modeling from the Committee for a Responsible Federal Budget, we estimate this proposal will cost roughly $200 billion over 10 years if made permanent, relative to allowing the pandemic PTC to expire at the end of this year.

CONGRESS MUST TACKLE THE REAL DRIVERS OF HEALTH COSTS

The other flaw with simply extending the pandemic PTC is that it doesn’t address the real problem of rising health-care costs, which have dramatically increased over time relative to the size of the economy. In 1963, health-care costs represented 5% of Gross Domestic Product (GDP). In 2025, they are projected to reach 18.5% of GDP. Today, the average cost of health care in the United States is estimated to be more than $16,500 per person, which historically has been nearly twice as much as the average cost of health care per person in other wealthy countries.

Expanding subsidies for a small slice of the population without tackling the drivers of high health-care costs will only fuel further price increases. When government assistance covers a larger share of premiums, insurers and providers face less pressure to control spending, allowing them to charge more knowing that taxpayers will pick up the bill. Prices climb in response, and costs to families and the federal budget escalate. It would therefore be both good policy and good politics to ensure that Americans who benefit from the PTC keep their health insurance while also confronting the structural reasons behind rising health-care costs.

Fortunately, there are smart reforms that policymakers can and should pair with any PTC expansion to both offset their cost to taxpayers and tackle the root causes of rising health-care costs. One place lawmakers should start is Medicare Advantage, which allows seniors to receive their Medicare benefits from private insurers rather than the federal government. While this program was originally intended to save money, it now costs taxpayers tens of billions of dollars per year because of loopholes that allow insurance companies to inflate their government reimbursements without increasing the quality of their care.

Through Medicare Advantage, insurance companies are paid based on the number of seniors they cover, plus an adjustment for enrollees’ “risk scores,” based on their health history. This mechanism was designed to compensate insurers for covering sicker, more expensive seniors. But insurers have manipulated the system through a practice called upcoding, which entails inflating patients’ risk scores with questionable diagnoses in order to make them appear sicker than they really are. Insurers use a variety of tactics to increase risk scores, including pushing patients to complete health risk assessments with company-employed providers and combing through patients’ medical records in chart reviews to look for diagnoses that doctors never reported.

In order to curb these overpayments, Congress should adopt key provisions from the bipartisan No UPCODE Act, introduced by Senators Cassidy (R-La.) and Merkley (D-Ore.). The first provision would block insurers from inflating risk scores with diagnoses from chart reviews and health risk assessments, unless they are confirmed in a medical setting, and the second would modify the risk adjustment formula to increase parity with traditional Medicare. Combined, these two changes would save $125 billion over 10 years, enough to offset more than half the cost of our PTC proposal. And if lawmakers went further to tackle all the causes of Medicare Advantage upcoding, they could increase their savings to $600 billion, enough to fully pay for our PTC and also begin to address our ballooning federal deficit. Forcing Medicare Advantage plans to boost profits through innovation rather than upcoding could unlock efficiencies from which non-Medicare patients could also benefit.

Expanding the use of site-neutral payments would tackle another perverse incentive currently built into Medicare. Every year, Medicare pays billions more for services performed in a clinic connected to a hospital than it does for similar services performed in a freestanding clinic. One report estimates that payments for preventative exams provided in a hospital outpatient department were 51% higher than payments provided in a freestanding physician’s office.

Since hospital systems still receive higher Medicare reimbursements when providing services in their lower-cost clinic settings, hospital systems are incentivized to buy up freestanding physicians’ offices so they can charge higher reimbursement rates. This swift trend toward consolidation and anti-competitive monopoly structure significantly increases costs to both taxpayers and patients, who are left with fewer cost-effective options for seeking care.

To address this problem, policymakers should work towards equalizing reimbursement rates between outside physician offices and hospital outpatient departments. CMS has some statutory authority to implement site-neutral payment policies and recently proposed ambitious reforms to advance site neutrality as well as other cost-saving measures for beneficiaries. But enacting legislation similar to a bipartisan bill introduced in 2023 would further expand site-neutral payments and could save taxpayers $175 billion over 10 years.

CONCLUSION

Instead of threatening to shut down the government over an outdated pandemic-era program, Democrats should be pressuring Republicans to meet them at a pragmatic middle-ground — one that permanently corrects the structural flaws of the original ACA in a fiscally responsible way. Doing so would signal to the American people that Democrats are serious about cutting medical costs rather than simply increasing government spending. PPI’s fix offers a balanced path forward: scale back the costly and regressive pandemic PTC expansion, smooth the benefit cliff, and pair any new spending with meaningful savings from reducing health-care costs. This combination of targeted assistance and real cost control would deliver more lasting affordability than another costly extension of overpriced subsidies.

This Week in RFK Jr.’s Vaccine Conspiracy Theories

Two high-profile meetings in Washington this week will shed light on Robert Kennedy Jr.’s controversial stewardship of the U.S. Department of Health and Human Services (HHS). Today, Sept. 17, Dr. Susan Monarez is appearing before the Senate HELP Committee to discuss her abrupt firing by Kennedy from her role as CDC Director last month. The hearing will be led by Senator Bill Cassidy (R-La.), a medical doctor and proponent of vaccines, who has begun to push back on Kennedy’s anti-vaccine actions at HHS. Then on Thursday and Friday, the Centers for Disease Control and Prevention (CDC) Advisory Committee on Immunization Practices (ACIP) will meet to discuss vaccine policy. This is the second meeting of ACIP since RFK Jr. fired all 17 members in June and replaced them with his handpicked appointees.

The thread connecting these two events is Secretary Kennedy’s crusade against vaccines, which is fueled more by conspiracy theories than science. His preference for quack medicine has gone far to discredit Kennedy’s Make America Healthy Again (MAHA) agenda in the eyes of public health professionals, if not President Trump.

That’s too bad, because MAHA contains some good ideas, such as working with companies to encourage healthier food and a comprehensive all-of-government approach to address the chronic disease epidemic, which has bipartisan support from Americans. Kennedy is aware of the popularity of these initiatives, which is why he is using MAHA as a Trojan horse to infiltrate his anti-vaccine, anti-science views into every federal health agency within HHS.

Despite his efforts, polls show that nearly 80% of Americans support requiring childhood vaccines. Moreover, Kennedy’s anti-vaccine theories clash with what is arguably the greatest achievement of Trump’s first term — Operation Warp Speed (i.e., the public-private partnership to accelerate the development of COVID-19 vaccines). A tightrope Kennedy has struggled to walk as Secretary of HHS.  

Kennedy initially praised Dr. Monarez, who was appointed by Trump and confirmed by the Republican Senate. However, she is expected to testify that Kennedy demanded she rubber-stamp any recommendations put through by his obliging new allies at ACIP. In an op-ed, Monarez predicted Kennedy would “discredit research, weaken advisory committees, and use manipulated outcomes to unravel protections” and generally seek to undermine the federal health review process.

Her testimony could put ACIP on the spot the next day. Historically, ACIP follows an evidence-to-recommendation framework, a targeted and transparent process of reviewing evidence to direct recommendations. However, observers expect the committee to abandon this framework when they review and update recommendations on previously well-vetted vaccines without receiving new evidence. If ACIP updates its guidance to better align with Kennedy’s inaccurate vaccine beliefs, as Dr. Monarez has predicted, it will make vaccines less accessible across the U.S., resulting in everyone being less healthy and safe.

The two events will illuminate Kennedy’s pernicious attempts to substitute crackpot theories for scientific rigor in determining the efficacy of vaccines. If Kennedy — and President Trump — get their way, it will likely prove injurious to the health of millions of Americans.

RFK Jr. Wants Us to Trust Health Tracking Devices and Apps. Should We?

As people are turning to health tracking devices and apps for understanding, tracking, and treating their health more than ever, current U.S. law has not evolved to protect this sensitive data. Despite this, Health and Human Services Secretary Robert F. Kennedy Jr. wants all Americans wearing health tracking devices by 2033, claiming it will improve health monitoring and detect disease earlier.

Wearables are any device worn by individuals to track health and activities. To function, these devices (e.g., smartwatches, fitness trackers) are connected to apps to allow a user to review their data. In addition, users can manually input data into apps. While wearable devices and their connected apps are already common in the U.S. and other countries, the scale of Kennedy’s plan raises serious data privacy and security concerns around how health data from these devices is collected, stored, and shared on their connected apps.

Many U.S. users are under the mistaken impression that health information collected through health tracking apps is protected by U.S. privacy laws. However, the main federal health privacy law, the Health Insurance Portability and Accountability Act (HIPAA), covers only health care providers, insurers, and their business partners. Commercial health apps fall outside HIPAA’s protection, which means they can legally collect and share user data ranging from daily steps to blood pressure to mental health diagnoses.

Without a national privacy law in place, it is unclear who controls and can use sensitive consumer data entered into these apps either manually or through a wearable device. For example, BetterHelp, a mental health and therapy app, was fined $7.8 million by the Federal Trade Commission (FTC) after it was found to have shared users’ sensitive mental health data with third-party advertising platforms, including Facebook and Snapchat. The FTC alleged BetterHelp violated §5 of the FTC Act for deceptive practices because the company assured customers their data would not be shared with third parties and conversations would be kept private.

In the European Union, the same platforms are held to stricter standards under the General Data Protection Regulation (GDPR). The GDPR, which many regard as unduly rigid, nonetheless holds organizations responsible for handling data, including requiring them to meet a lawful basis for processing data and being held accountable when not meeting these standards. For example, Fitbit, a widely used health tracking app connected to Google wearable devices, but is usable without a device, must receive explicit consent from users before processing health data.

U.S. law and regulatory policy have not been meaningfully updated to account for the rise of artificial intelligence and digital health technology. In 2021, Senator Jacky Rosen (D-Nev.) and Senator Bill Cassidy (R-La.) introduced the SMARTWATCH Data Act. The aim was to ensure health data collected by wearables through their connected apps would be protected under similar standards that apply to traditional health data. But the bill did not advance past committee.

Congress needs to create a federal framework to enforce data privacy before RFK Jr. moves forward with a national wearable initiative. Although the FTC has taken action against individual companies, fines on large companies are typically viewed as a slap on the wrist. Consumers need a new federal law to stop companies from collecting and selling data once wearable apps are downloaded. Wearables and their connected apps offer real benefits, such as early detection and long-term tracking of chronic conditions; however, privacy, consent, and data transparency must come first.

Without updated data laws, Americans will continue to be vulnerable to the misuse of their health data. Data such as fertility, heart rate, and sleep patterns will become a valuable, sellable commercial product to companies. This kind of mass data collection risks creating a system that prioritizes profit over user safety. The Trump administration should not pile more risk on consumers by failing to protect the privacy and security of health tracking devices and apps.

Ware for The Hill: Republicans are Making Boogeymen of Their Own Voters on Medicaid

Republicans love their boogeymen; the grotesquely exaggerated villains they use to justify their worst policy ideas. President Trump loves to parade his favorite boogeymen: the “criminal aliens,” the dishonest media, the Democrats, and so on. These dehumanizing caricatures help him rile up his base and lead them to back his cruelest initiatives.

As the GOP-controlled Congress argues the merits of the cuts included in Trump’s “big, beautiful bill” act — which is deeply unpopular with voters — they’re discovering new boogeymen to deflect criticism.

Republicans are very defensive about their $1 trillion cut in Medicaid, which will deprive almost 12 million, mostly low-income and working-class Americans, of their health care coverage.

Keep reading in The Hill.